Stem Cells for Knee Pain: How They Work and When They Help
2026-09-03 · 8 min read
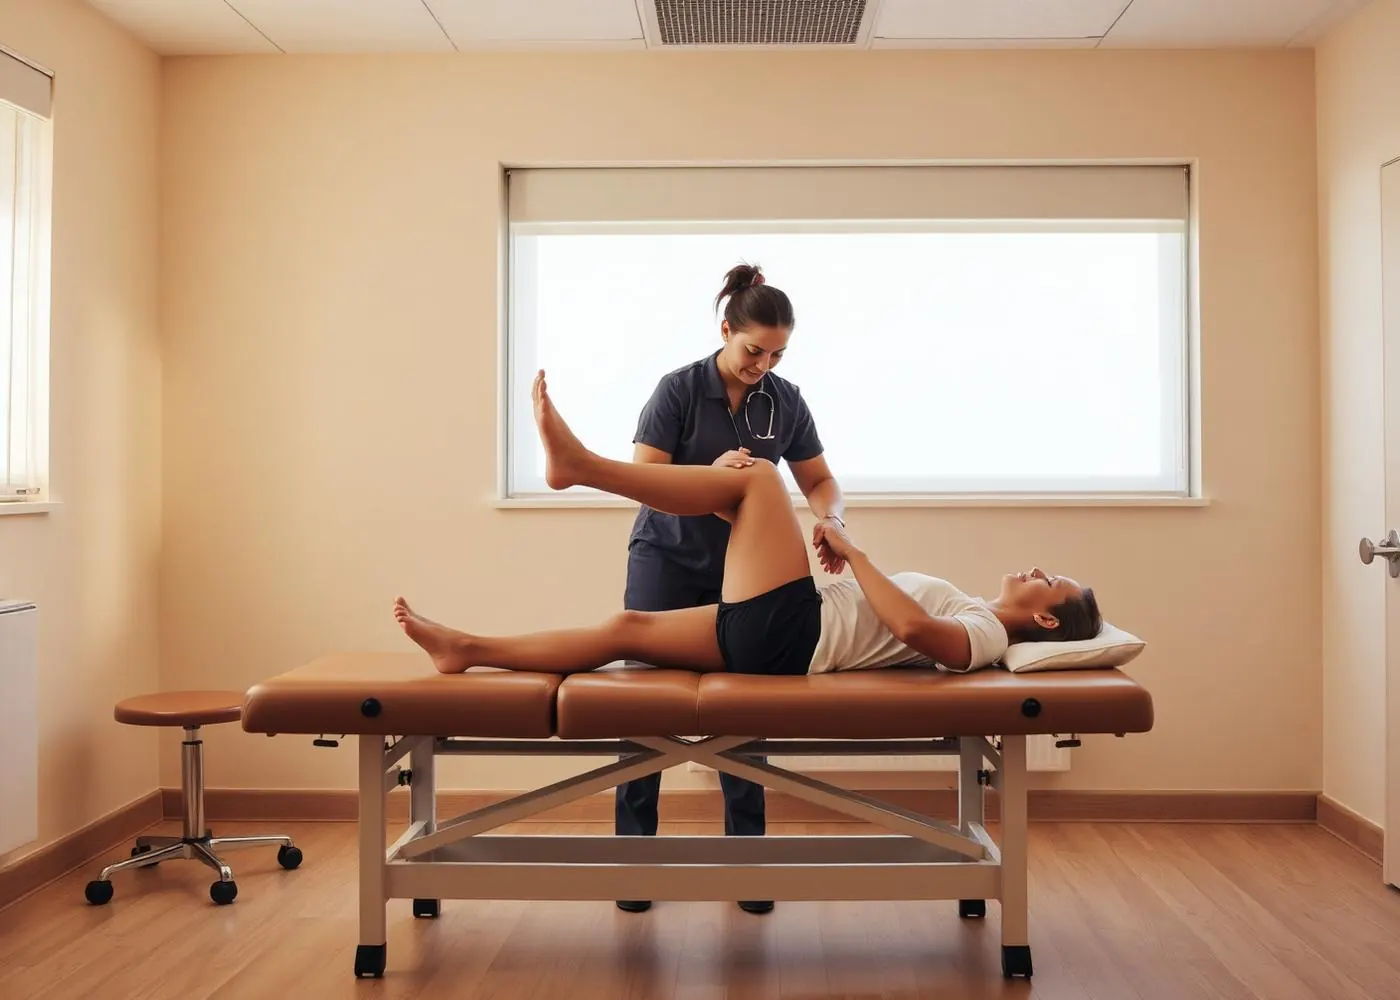
Knee pain is one of the most common reasons people consider regenerative therapy. Here is what the cells actually do inside the joint, and when the evidence suggests they are worth considering.
Medically reviewed by the Bangkok Stem Cell Center medical team
If your knee hurts on stairs, after sitting, or during the first steps of the morning, you have probably already tried the standard options: rest, anti-inflammatories, physiotherapy, perhaps an injection of cortisone or hyaluronic acid. When those stop working, regenerative medicine starts to sound interesting. This article explains what stem cell therapy for knee pain actually involves, how it is thought to work, and the honest limits of what it can do.
Why the knee breaks down first
The knee is a weight-bearing hinge with almost no margin for error. It absorbs forces equal to several times your body weight with every step, and it depends on a thin layer of cartilage, two meniscal shock absorbers, and a set of ligaments that all have poor blood supply. Once cartilage or meniscus is damaged, the joint's own repair tools are limited, which is why knee problems tend to become chronic rather than resolving cleanly.
Osteoarthritis is the most common endpoint: the cartilage surface gradually thins, the underlying bone becomes stressed and sometimes swollen, and the lining of the joint — the synovium — stays inflamed. That inflammation is what hurts, and it is also what accelerates further damage. Breaking that cycle is the central goal of most non-surgical knee treatments.
What 'stem cells' means in this context
In knee therapy, the cells most often discussed are mesenchymal cells, usually shortened to MSCs. These are adult repair cells, not embryonic cells. They do not transform into a new knee joint. What they appear to do is coordinate the local environment: they release signalling molecules that calm excessive inflammation, encourage new blood vessel formation, and prompt resident cartilage and tendon cells to become more active.
Think of them less as replacement parts and more as project managers. They arrive at a noisy, inflamed construction site and help the existing crew work more effectively. That is why the best results are usually seen in knees that still have some viable tissue left to work with, rather than in joints that have already worn down to bone on bone.
How the cells are delivered
There are two main approaches. The first, and most common for isolated knee problems, is an intra-articular injection: the cells are placed directly into the joint space, often under ultrasound or fluoroscopic guidance so the needle lands in the right compartment. The second is an intravenous infusion, used when the goal is broader — for example, when a patient has multiple joints involved or significant systemic inflammation alongside the knee.
Some protocols combine both. A local injection addresses the knee directly, while an intravenous dose supports the overall inflammatory environment. Platelet-rich plasma or exosomes may be added as reinforcement, though the evidence for those combinations is earlier and less consistent than for cellular therapy alone.
Why it may help, in plain terms
The proposed benefits fall into three categories. First, pain reduction. By damping the inflammatory signals inside the joint, many patients report that the knee feels less swollen and less tender, sometimes before any structural change is visible on imaging. Second, functional improvement: less fluid in the joint, better range of motion, and more confidence on stairs or uneven ground. Third, disease modification: the hope, supported by some though not all studies, that the therapy can slow further cartilage loss by changing the biological environment rather than just masking symptoms.
It is important to separate these carefully. Pain relief is the most consistently reported outcome in clinical trials. Structural regrowth of cartilage, while documented in some case series and small studies, is far less predictable and usually modest when it occurs.
What the research actually shows
Several randomised trials and systematic reviews have looked at MSC therapy for knee osteoarthritis. The overall picture is cautiously positive: on average, patients report meaningful pain improvement for six to twelve months, and in some studies up to two years. The effect size is generally larger than hyaluronic acid and comparable or better than some other injectable options in the same timeframe.
There are caveats. Study quality varies, dosing and cell source differ between trials, and the placebo response in knee injections is notoriously strong. Some of the early enthusiasm came from small, uncontrolled studies. Larger, longer trials are still needed to confirm whether the benefits last beyond a few years and whether repeat dosing adds value.
For meniscal tears and ligament injuries, the evidence is more limited. Cellular therapy is sometimes used to support healing in patients who are not surgical candidates or who want to avoid surgery, but it is not a replacement for repair when the mechanical problem is severe.
Who tends to respond best
- Patients with mild to moderate osteoarthritis, where some cartilage still remains
- Those with stable knees — no severe deformity or major ligament failure
- People whose pain is driven mainly by inflammation rather than pure mechanical wear
- Individuals in reasonable general health, without uncontrolled diabetes or active infection
- Patients willing to follow the aftercare plan, including loading and physiotherapy
Who is less likely to benefit
No honest clinic should promise results to everyone. Advanced osteoarthritis with bone-on-bone contact, significant joint deformity, or a knee that is mechanically unstable is unlikely to respond well to injections alone. In those cases, the realistic discussion is usually about partial or total knee replacement, or other surgical options.
Active infection, cancer, or conditions that require strong immunosuppression are also reasons to delay or avoid cellular therapy. And if the pain is actually coming from the hip or the lower back, treating the knee will not help no matter how good the cells are.
What the treatment week looks like
A typical program at a specialist centre begins with a consultation and review of imaging, not with a needle. The physician needs to confirm that the knee is the source of the problem and that there is enough tissue left to justify a biological approach. Blood tests may be arranged to rule out issues that would change the plan.
The injection itself is usually done under sterile conditions with local anaesthetic. It takes only a few minutes, though patients are often observed briefly afterwards. There may be mild soreness for a few days, which is a normal inflammatory response. Most people are encouraged to keep walking gently but to avoid high-impact activity or deep bending for a short period.
If intravenous cellular therapy is part of the protocol, it is usually delivered as a slow infusion over one to two hours across one or more days. The whole program commonly fits into three to five days, which is why it suits international patients.
The realistic timeline
Cellular therapy is not a same-day painkiller. The first two weeks are often quiet, and some patients feel slightly worse before they feel better because of the post-injection inflammatory response. Noticeable comfort improvements usually appear between four and twelve weeks, with the clearest change around the three-month mark.
This slow onset surprises some patients, but it makes sense biologically. Cells need time to signal, local inflammation needs to settle, and resident tissue needs to respond. A patient who expects instant relief is likely to be disappointed; one who understands the timeline is more likely to notice the gradual improvements.
How to judge a clinic offering this
- Does a licensed physician examine you and review your imaging, or does a salesperson quote a price first?
- Can the clinic show you cell source, count, viability, and processing documentation?
- Are you given a written plan with total cost before payment?
- Has anyone explained a scenario in which this would not be suitable for you?
- Is follow-up scheduled, and is it included in the cost?
The honest bottom line
Stem cell therapy for knee pain is a promising option for the right patient, not a miracle cure for every knee. It works best when the joint still has biological activity to work with, when inflammation is a major part of the problem, and when expectations are realistic about timing and degree of improvement.
If you are considering it, start with a proper assessment of your knee and an honest conversation about whether you are likely to benefit. Any clinic that promises to regrow cartilage in every patient, or that quotes a price before looking at your imaging, is selling hope rather than medicine.
This article is general educational information and is not a substitute for personalised medical advice. If you would like a physician's view on whether regenerative therapy is appropriate for your knee, contact a qualified clinical team with your recent imaging and history.
Reviewed by Bangkok Stem Cell Center Medical Team | Last updated: October 2026
Travelling to Bangkok During Cancer Treatment: A Medical Planning Checklist
Travel during cancer treatment requires more than a flight and hotel. This checklist helps patients coordinate records, medicines, safety and follow-up before leaving home.
Considering Cancer Immunotherapy in Bangkok? Questions to Ask Before You Travel
The word immunotherapy covers very different treatments. Before travelling, establish exactly what is proposed, why it fits the diagnosis, and who will manage complications.
